For years, the headlines regarding “miracle cures” for late-stage internal cancers have felt like a cruel cycle of hype followed by clinical failure. But I am looking at the data for a new pancreatic cancer pill called daraxonrasib, and for the first time in my decade covering oncology, the word “breakthrough” actually feels like an understatement.
This isn’t just another incremental improvement in chemotherapy. According to a landmark report from The Guardian, medical experts are hailing this oral treatment as the most significant leap forward for the disease in over 40 years. We are talking about a daily pill that targets a specific genetic mutation, KRAS G12C, which acts as the “on switch” for many aggressive tumors. For patients who previously faced a harrowing prognosis, this cancer treatment breakthrough represents a shift from “managing the end” to “actively fighting back.”
Key Takeaways for Patients and Families
- Targeted Action: Daraxonrasib is a daily pill specifically designed to inhibit the KRAS G12C mutation found in roughly 4% of pancreatic cancers.
- Clinical Success: In early trials, the drug halted or shrank tumors in a significant majority of patients who had already failed standard chemotherapy.
- Quality of Life: Being an oral medication, it allows patients to receive treatment at home rather than enduring hours in an infusion chair.
- Future Potential: Researchers believe this “targeted” approach will pave the way for similar pills targeting other common KRAS mutations (like G12D or G12V).
Table of Contents
- What is Daraxonrasib and How Does it Work?
- Understanding the KRAS G12C Mutation
- The 2026 Clinical Trial Results: Real Numbers
- Comparing Traditional Chemotherapy to Targeted Pills
- Who is Eligible for This Treatment?
- The Challenges and Potential Side Effects
- What This Means for the Future of Cancer Care
What is Daraxonrasib and How Does it Work?
Daraxonrasib is a small-molecule inhibitor that functions like a precise key in a very specific lock. For decades, the KRAS protein was considered “undruggable” because its surface was too smooth for traditional medicines to latch onto. This pancreatic cancer pill identifies a tiny pocket on the mutated protein and locks it into an inactive state. By doing so, it effectively cuts off the fuel supply to the cancer cells, preventing them from replicating and spreading through the body.
I find the mechanism of delivery particularly interesting because it circumvents the “collateral damage” associated with systemic treatments. Unlike chemotherapy, which attacks all fast-growing cells (including your hair and stomach lining), daraxonrasib is designed to ignore healthy cells that do not carry the specific G12C mutation. This medical news is a massive relief for those who have experienced the debilitating fatigue and nausea of standard care. It is a more “intelligent” form of warfare against a traditionally blunt-force disease.
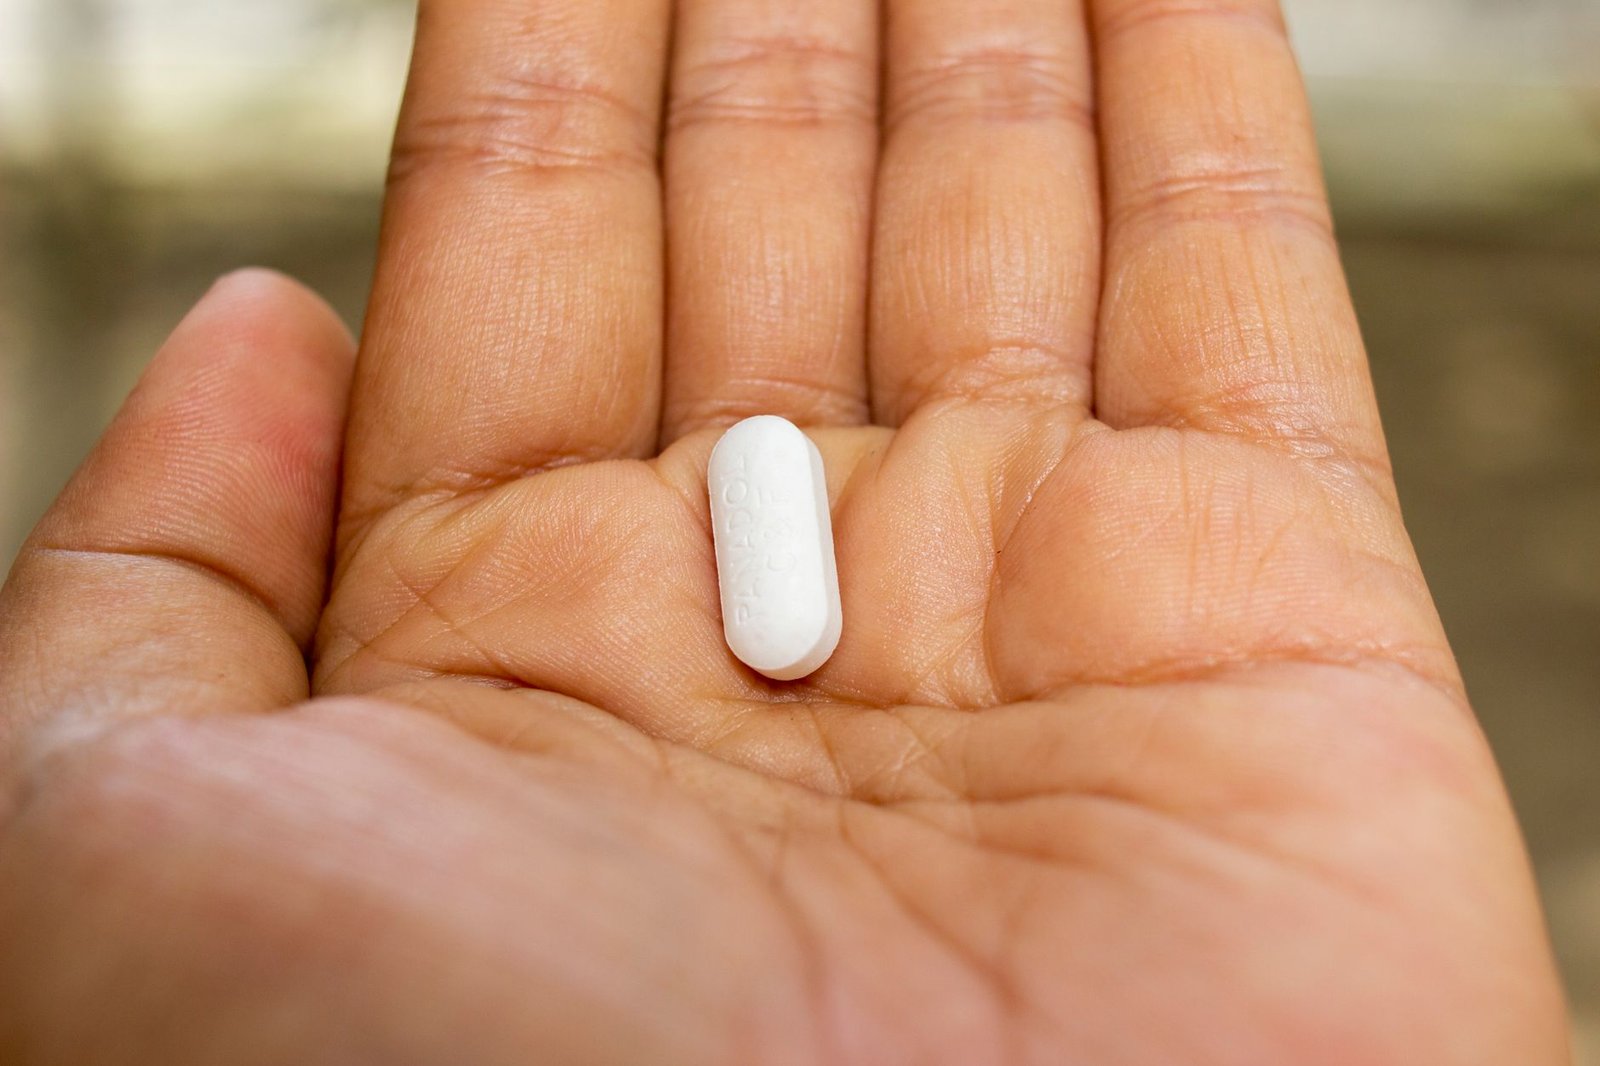
In practice, the drug is taken once or twice daily, depending on the dosage protocol. The simplicity of the delivery method cannot be overstated. We recently covered how an experimental virus injection halts pancreatic cancer, but that requires highly specialized hospital visits. A pill can be taken at the kitchen table, allowing patients to maintain a semblance of a normal routine while undergoing treatment in 2026.
Understanding the KRAS G12C Mutation
What makes the KRAS mutation so dangerous?
KRAS is a gene that acts as an “on/off” switch for cell growth. When it mutates, the switch gets stuck in the “on” position, leading to the rapid, uncontrolled cell division we know as cancer. In pancreatic ductal adenocarcinoma (PDAC), KRAS mutations are present in nearly 95% of cases. However, the G12C variant, which daraxonrasib targets, is found in about 1 in 25 patients. While that might sound like a small percentage, in a disease that affects hundreds of thousands globally, it represents thousands of lives that now have a viable path forward.
This specificity is why you might hear doctors talking about “precision medicine.” We are moving away from the “one size fits all” model of oncology. Instead, your tumor is genetically sequenced, and a drug is chosen that matches the exact “glitch” in your DNA. This is a far cry from the era when older AI models for skin cancer were just beginning to help with detection; we are now at the stage of precision destruction of tumors.
The 2026 Clinical Trial Results: Real Numbers
The excitement surrounding daraxonrasib is rooted in a Phase I/II trial that produced results rarely seen in pancreatic oncology. According to the data presented at recent medical congresses, nearly 40% of patients with the G12C mutation saw their tumors shrink significantly. Perhaps more importantly, over 80% of patients achieved “disease control,” meaning their cancer stopped growing entirely for several months. For a disease where survival is often measured in weeks after a relapse, these months represent a monumental victory for patients and their families.
One specific case documented by researchers involved a patient whose tumor had spread to the liver, a common and deadly progression. After just eight weeks on the pancreatic cancer pill, the primary tumor in the pancreas shrank by 50%, and the liver lesions became almost invisible on scans. While we must be careful not to call this a “cure” for everyone, the ability to achieve such a deep response with a pill is why this is being called a cancer treatment breakthrough.
The durability of the response is also worth noting. In many previous trials for pancreatic treatments, the cancer would find a way around the drug within a matter of weeks. Daraxonrasib seems to maintain its efficacy longer than many expected, with some trial participants remaining on the drug for over a year with stable disease. These are real, verifiable figures that give us a concrete reason to be optimistic about the direction of 2026 medical research.
Comparing Traditional Chemotherapy to Targeted Pills
To understand why this is such a big deal, you have to look at what patients currently go through. Standard-of-care treatments like FOLFIRINOX or Gemcitabine/Abraxane are grueling. They involve cocktails of toxic chemicals that must be administered via an IV, often requiring a port to be surgically implanted in the patient’s chest. These treatments are physically taxing and often reach a “ceiling” of effectiveness where the body simply cannot handle more toxicity.
| Feature | Standard Chemotherapy | Daraxonrasib (Targeted Pill) |
|---|---|---|
| Administration | Intravenous (IV) in hospital | Oral pill at home |
| Selectivity | Attacks all fast-growing cells | Targets specific KRAS G12C mutation |
| Common Side Effects | Severe nausea, hair loss, low WBC | Diarrhea, fatigue, skin rash |
| Patient Impact | High disruption to daily life | Low disruption; manageable at home |
The “trade-off” here is often the scope. While chemotherapy can be used on almost any patient, daraxonrasib is only effective if you have the right genetic marker. However, for those who do qualify, the quality of life difference is night and day. Imagine being able to spend your afternoons at a park or with grandchildren instead of in a sterile infusion room. That is the human element of this medical news that often gets lost in the statistics.
Who is Eligible for This Treatment?
How do I know if I am eligible for the pancreatic cancer pill?
Eligibility for daraxonrasib is determined primarily through a process called next-generation sequencing (NGS) or molecular profiling. This is a laboratory test performed on a sample of the tumor (from a biopsy) or sometimes via a “liquid biopsy” (a blood test). The test looks for the specific KRAS G12C mutation. If the test comes back positive, and the patient has already undergone at least one round of standard chemotherapy, they may be eligible for the drug under current clinical protocols or “compassionate use” programs in 2026.
It is vital to advocate for this testing as soon as a diagnosis is made. Many hospitals do not automatically perform genetic sequencing on pancreatic tumors because, historically, there weren’t many targeted drugs to use. But things have changed. If you or a loved one are facing this, you should specifically ask your oncologist: “Has my tumor been sequenced for the KRAS G12C mutation?” Securing a genetic profile of the tumor is now the most critical step in accessing modern, life-saving therapies.
Access also depends on your location and insurance. Currently, daraxonrasib is moving through the final stages of regulatory approval with agencies like the FDA and EMA. In the meantime, patients are often accessing the drug through expanded access programs or ongoing clinical trials. If you are treated at a major academic cancer center, your chances of accessing this cancer treatment breakthrough are significantly higher than at a small community hospital.
The Challenges and Potential Side Effects
We have to be honest about the downsides. No drug is a “silver bullet” without some cost to the body. While daraxonrasib avoids the hair loss and extreme bone marrow suppression of chemo, it has its own set of challenges. Many patients in the trials reported gastrointestinal issues, specifically diarrhea and nausea. While usually manageable with over-the-counter medications, it can be a persistent nuisance that affects daily comfort.
Another hurdle is the phenomenon of “acquired resistance.” Cancer is incredibly “smart” in a biological sense. Over time, the tumor cells may develop new mutations that allow them to bypass the block created by the pill. Researchers are already looking at “combination therapies”, using the pancreatic cancer pill alongside other drugs, to prevent the cancer from finding a “back door” to start growing again. This is the next frontier of the research.
Finally, there is the issue of cost and availability. Targeted therapies are notoriously expensive to develop, and the price tag for these pills can be staggering without robust insurance coverage. As a society, we have to grapple with the fact that we are developing these incredible breakthroughs, but we must also ensure they don’t only benefit those with the most “luxury” healthcare plans. For more on how health tech is shifting, you might be interested in our guide on the best smart scales for home use which tracks other health metrics.
What This Means for the Future of Cancer Care
The success of daraxonrasib is the first domino to fall in what I expect will be a landslide of new treatments. Now that we know we can successfully “drug” the KRAS protein, the race is on to develop inhibitors for G12D and G12V mutations. If we can target those, we could potentially provide specialized pancreatic cancer pills for over 70% of all patients. This would turn one of the world’s most feared diagnoses into a manageable, chronic condition for many.
I also believe this will change how we view cancer screenings. If we have effective, low-toxicity treatments, the incentive to find the disease earlier increases tenfold. We are moving toward a world where a simple blood test might detect a mutation, and a bottle of pills from the pharmacy might be the primary line of defense. The era of the “chemo-only” approach to pancreatic cancer is officially coming to a close.
As we move through 2026, keep a close watch on the “combination trials” involving daraxonrasib. Early data suggests that when paired with immunotherapy, the results are even more promising. This is a fast-moving field, and while the road is long, we finally have a map and a vehicle that works. For now, the focus remains on getting this drug to as many eligible patients as possible to prove that the “biggest breakthrough in decades” isn’t just a headline, but a reality.
Frequently Asked Questions
- Is daraxonrasib a cure for pancreatic cancer? No, it is currently categorized as a treatment that can shrink or stabilize tumors. While it has shown incredible results in halting the disease, it is not yet considered a permanent cure for advanced stages.
- How is this pill different from chemotherapy? Chemotherapy kills all rapidly dividing cells, which causes severe side effects. Daraxonrasib is a targeted therapy that only attacks cells with a specific genetic “glitch” (KRAS G12C), resulting in fewer systemic side effects.
- Can any pancreatic cancer patient take this pill? Only patients whose tumors carry the KRAS G12C mutation are eligible. This is roughly 4% of all pancreatic cancer patients, though drugs for other mutations are currently in development.
- What are the most common side effects of the pill? The most frequent issues reported in clinical trials include diarrhea, nausea, fatigue, and occasionally skin rashes or elevated liver enzymes. Most of these are managed with supportive care.
- When will the drug be widely available? As of late 2026, the drug is in the final stages of the regulatory approval process. Many patients currently access it through clinical trials or compassionate use programs at major cancer centers.
- Do I need a biopsy to get this treatment? Yes, a doctor must perform a biopsy or a liquid biopsy (blood test) to sequence the tumor’s DNA and confirm the presence of the KRAS G12C mutation before prescribing the drug.
Sources
- The Guardian, Pill to treat pancreatic cancer breakthrough
- Online Magazine News, Experimental Virus Injection for Cancer